
Clinical Findings Associated with EEHV Hemorrhagic Disease in Elephants
Updated July 2026
General Introduction:
It is now well recognized that clinical signs associated with Elephant Endotheliotropic Herpesvirus Hemorrhagic Disease in Elephants (EEHV HD) may appear up to 4 weeks after a calf has been infected. Clinical disease can have a rapid onset and progression, and some calves have died within 10 hours of the first observation of clinical signs. The timing of infection, especially a primary infection, is therefore critical and can only be recognized with ongoing routine monitoring. Since the viral cellular targets are capillary endothelial cells, clinical signs will reflect the compromised cardiovascular system, coagulopathy, shock, and associated multi-organ dysfunction.
In some individuals that survived EEHV HD, clinical signs generally worsened for 1-2 days after the initiation of therapy and slowly dissipated over the course of 10-15 days. EEHV HD most commonly affects Asian elephants between 1 and 8 years of age and African elephants between 1 and 15 years of age. Clinical disease has been observed in Asian elephants older than 8 years, but less frequently.
Initial observations in an elephant ill from EEHV HD are often vague and can easily be attributed to other conditions. In most cases the first observation is lethargy, decreased appetite, or both, lameness and or joint stiffness. It is tempting to attribute decreased activity level or lameness to a bout of rough play or decrease in food or water consumption to a recent tusk eruption or mild colic. It is imperative that animal care staff be alert for any changes in an elephant calf’s condition and to assume illness is due to EEHV HD until proven otherwise.
Training Observations:
One behavior observed by elephant managers in elephant calves ill from EEHV HD is that the calf demonstrates less compliance than usual during training sessions. It has also been observed that calves ill from EEHV HD are more attached to the herd and more reluctant to separate from the group than usual.
Clinical Observations:
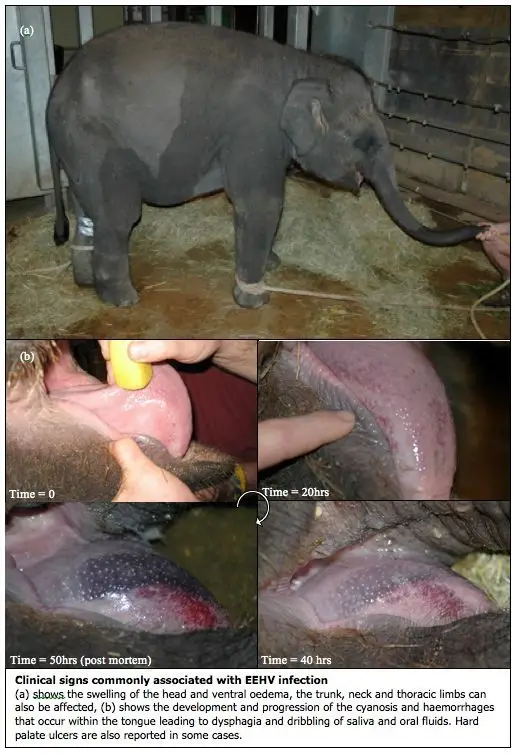
The following clinical signs have been observed in elephants ill from EEHV HD. The presence of more than 1 or 2 categories of signs makes EEHV more likely, and treatment should be initiated and continued until diagnostic test results are available:
- Decrease in food or water intake.
- Alteration in sleeping pattern or activity: more than 20% change in activity level from baseline. This can mean sleeping more OR sleeping less, as some calves appear reluctant to lay down when they are ill.
- Mentation change: the elephant appears confused or is demonstrating other neurologic signs
- Signs of discomfort or acute pain (either abdominal or musculoskeletal)
- Abdominal: stretching, rolling
- Musculoskeletal: lameness / stiffness
- Changes in fecal output such as diarrhea, decreased stool production, hard stools, or constipation
- Oral lesions:
- Hyperemic or dark red oral mucosa
- Vesicle formation or ulceration
- Petechiae / ecchymoses
- Ocular abnormalities:
- Scleral injection
- Icteric sclera
- Retinal hemorrhage
- Temporal gland swelling
The presence of edema or cyanosis, even if not accompanied by any of the above clinical signs, should warrant initiation of treatment immediately:
**Edema: swelling or fluid accumulation visible grossly, particularly head, trunk, neck. This excludes the presence of ventral or dependent edema, which is considered a non-specific finding associated with many etiologies in elephants
**Cyanosis: present on tongue or other mucus membranes
Physiologic parameters:
Physical examination of an elephant suspected to be ill from EEHV HD may further reveal the following abnormalities:
- Cardiovascular abnormalities: (must know elephant’s baseline information)
- Tachycardia
- Arrhythmia
- Heart murmur
- Changes in blood pressure (must know elephant’s baseline information)
- Pulse oximetry < 95% (as measured on the lip)
- Alteration in body temperature (above or below normal, must know elephant’s baseline) as measured by fresh fecal bolus temperature or “life chip” microchip body temperature.
- Evidence of fluid accumulation as noted on ultrasound examination:
- Abdominal fluid
- Pericardial fluid
Clinical Pathology:
Evaluation of the complete blood cell count (CBC) in an elephant suspected of being ill from EEHV HD can yield very helpful information. It is most helpful when the normal ranges of the CBC values are known for the individual elephant in question since there is known to be considerable inter-elephant variation in values. It is important to always compare an elephant’s bloodwork to its own reference intervals. The presence of any of the abnormalities listed below is indication that an elephant should be started on EEHV therapy until confirmatory PCR results are available:
Leukopenia: One of the early changes in affected animals is a leukopenia with monocytopenia. In many cases of EEHV associated illness the total white blood cell count (WBC) dropped significantly just before, or at the same time as, viremia increased significantly. In several recent, closely monitored cases of EEHV-associated illness, the total WBC was found to be decreased for one to five days, then started to increase, and was followed by a rebound leukocytosis for several days or weeks as the individual entered the recovery phase.
Monocytopenia: Typically, the most abundant white blood cell in elephants is the monocyte. In cases of acute EEHV HD, as well as in other infections, neutrophils/heterophils may outnumber the monocytes and become the predominant cell type. This is abnormal and should be considered significant. A drop in the monocyte to neutrophil/heterophil ratio, especially a drop below 1, should be taken seriously.
Band cells: The presence of any immature neutrophils/heterophils (band cells) on a blood smear is abnormal in elephants; this is clinically significant and indicates a serious disease process, whether EEHV HD or another condition.
Thrombocytopenia: Since EEHV targets and damages endothelial cells, blood vessels become leaky resulting in internal hemorrhage. Thrombocytes (platelets) are activated to stop the leaking resulting in thrombocytopenia (due to consumption) and resulting coagulopathy. Often, a rebound thrombocytosis will occur in the recovery phase.
The presence of leukocytopenia, a decrease in absolute monocyte number (or a predominance of neutrophils/heterophils), a drop in the monocyte to neutrophil ratio, or thrombocytopenia in an elephant with any degree of EEHV viremia should be considered significant, and therapy should be initiated immediately and continued until PCR results are available.
Serial monitoring of whole blood EEHV PCR and WBC and differential count in an elephant affected by EEHV HD provides a very useful tool for gauging decisions on extent and duration of therapy.
Evaluation of an elephant’s serum biochemistry profile and urinalysis are important for assessing the overall health of the animal and informing supportive treatment. To date significant biochemical abnormalities that specifically indicate illness associated with EEHV HD have not been identified.
Increase of serum amyloid A (SAA), an acute phase protein, has been associated with EEHV-1 viremia over 10,000 vge/ml in Asian elephants. The Avian and Wildlife Laboratory of the Comparative Pathology Lab at the University of Miami (http://cpl.med.miami.edu/avian-and-wildlife/) will test serum for SAA.
Determination of coagulation status and clotting times should be considered in elephants suspected of illness associated with EEHV HD. Normal coagulation profiles of the Asian and African elephants established when the animal is healthy can further guide the interpretation abnormalities noted during the disease process and help with treatment decision.
Molecular Diagnostics:
The gold standard for diagnosis of EEHV HD is whole blood PCR. There are two types of PCR, conventional (cPCR)and quantitative (qPCR). See the Diagnostics page for more details about their similarities, differences, and how to use results from each type of PCR appropriately.
In North America, EEHV 1A is the most common EEHV species associated with EEHV HD in Asian elephants and should be the first virus tested for in a sick elephant. EEHV 1B, EEHV 4 and EEHV 5 have been associated with clinical illness in Asian elephants less frequently. EEHV 2 and EEHV 3A, EEHV 3B, EEHV 6, and EEHV 7 have been associated with illness in African elephants. The National Elephant Herpesvirus Laboratory and Baylor College of Medicine have the capability to test for all known EEHV viruses by PCR (click here to see list of EEHV testing laboratories).
Detecting DNA in whole blood, a viremia, does not necessarily mean an elephant has EEHV HD. Through routine monitoring of elephants in several North American institutions, we have learned that some degree of recrudescent EEHV viremia can be detected in clinically healthy elephants (see Managing Recrudescence for more information ). Typically, these viremias remain at a low level and may last days to weeks. Therefore, the presence of EEHV viremia alone, particularly in a subclinical elephant, is not in itself confirmation of EEHV HD. Viremia should be interpreted in conjunction with the CBC values and serological status of the animal. If an animal has antibodies to the type of EEHV in the blood, that animal is likely experiencing a recrudescent viremia. If an elephant has a low viremia (<5,000 vge/mL), no clinical signs, and no CBC changes, serial monitoring of the viral loads (and close physical observation of the elephant) is recommended to determine if the viremia is increasing exponentially. If an elephant develops a viremia but is seronegative for that species or type of EEHV it is recommended to monitor viremia closely for exponential increase and potentially start treatment immediately if viremia increases. The trend of the viremic load is more important than the absolute number, with a rapid, exponential increase in viremia indicating a need for aggressive therapy and close monitoring.
Trunk washes also can be submitted for EEHV PCR (click here to see list of EEHV testing laboratories). Following a viremia or recrudescence event, it has been observed that elephants will secrete large amounts of EEHV DNA from their trunks for several weeks up to a year or more. Trunk wash fluid can be centrifuged and the pelleted material evaluated for EEHV DNA via PCR. This can confirm shedding of EEHV and can be epidemiologically useful, but does not provide any clinically significant information that would help in diagnosing illness associated with EEHV HD.
Selected References:
Atkins L, JC Zong, J Tan, A Mejia, SY Heaggans, SA Nofs, JJ Stanton, JP Flanagan, L Howard, E Latimer, MR Stevens, DS Hoffman, GS Hayward, and PD Ling. 2013. Elephant endotheliotropic herpesvirus 5, a newly recognized elephant herpesvirus associated with clinical and subclinical infections in captive Asian elephants. J Zoo Wildl Med 44(1): 136-134.
Bauer KL, Latimer E, Finnegan M. 2018 Long-term, intermittent, low-level elephant endotheliotropic herpesvirus 1A viremia in a captive Asian elephant calf. J Vet Diagn Invest. 30(6):917-919.
Boonprasert K, Srivorakul S, Monchaivanakit N, Langkaphin W, Sripiboon S, Janyamethakul T, Srisa-ad C, Guntawang T, Brown JL, Thitaram C, Pringproa K. 2024. Characterizations of Elephant Endotheliotropic Herpesvirus Type 1A and 4 Co-Infections in Asian Elephant (Elephas maximus) Calves. Veterinary Sciences, 11(4), 147.
Bronson E, McClure M, Sohl J, Wiedner E, Cox S, Latimer EM, Pearson VR, Hayward GS, Fuery A, Ling PD. 2017. Epidemiologic evaluation of elephant endotheliotropic herpesvirus 3b infection in an African elephant (Loxodonta africana). J Zoo Wildl Med 48(2), 335-343.
Fayette MA, Minich DJ, Sylvester H, Latimer E. First detection of clinical disease due to elephant endotheliotropic herpesvirus 7a in two African elephants (Loxodonta africana) in human care. J Zoo Wildl Med. 2024 Mar;55(1):290-294.
Gentry PA, ML Ross, and M Yamada: Blood coagulation profile of the Asian elephant (Elephas maximus) In Gentry PA, Ross ML, Yamada M: Zoo biology, Vol 15, New York, 1996, Wiley-Liss, pp 413-423.
Heniff AC, Lynch AM, Ruterbories LK, Minter LJ, Georoff TA, Balko JA. 2024. Investigation of a point-of-care viscoelastic coagulation monitor and its comparison to thromboelastography in clinically healthy African elephants (Loxodonta africana). J Zoo Wildl Med 55(1):164-172.
Isaza R, Wiedner E, Hiser S, Cray C. 2014. Reference intervals for acute phase protein and serum protein electrophoresis values in captive Asian elephants (Elephas maximus). J Vet Diagn Invest26(5), 616-621.
Iyer ML, Molter CM, Flanagan JP, Bauer KL, Bernardy R, Hoffman D, Parkinson L, Brainard BM, Smiley Evans T, Pursell T, Ling PD. 2022. Novel diagnostic and therapeutic approaches to elephant endotheliotropic herpesvirus 1a hemorrhagic disease in a captive juvenile Asian elephant (Elephas maximus). J Zoo Wildl Med 53(1), 232-240.
Knüppel S, Balfanz F, Riedel C, Strauss V, Hoornweg TE, Dimmel K, Walk K, Kübber-Heiss A, Posautz A, Voracek T, Abdelgawad A, Trimpert J, Hering-Hagenbeck S, Rümenapf T, Auer A. 2025. Severe Elephant Endotheliotropic Herpesvirus 6 Associated Disease in Two African Elephants Under Human Care in Austria. Animals (Basel). 20;15(10):1482.
Stanton JJ, C Cray, M Rodriguez, KL Arheart, PD Ling, and A Herron. 2013. Acute phase protein expression during elephant endotheliotropic herpesvirus-1 viremia in Asian elephants (Elephas maximus). J Zoo Wildl Med 44(3): 605-612.
Stanton J, JC Zong, C Eng, L Howard, J Flanagan, M Stevens, D Schmitt, E Wiedner, D Graham, RE Junge, MA Weber, M Fischer, A Mejia, J Tan, E Latimer, A Herron, GS Hayward, and PD Ling. 2013. Kinetics of viral loads and genotypic analysis of elephant endotheliotropic herpesvirus-1 infection in captive Asian elephants. J Zoo Wildl Med 44(1): 42-54.
Wiedner E, L Howard and R Isaza. 2012. Treatment of elephant endotheliotrophic herpesvirus (EEHV). In: Fowler, ME and RE Miller (eds) Zoo and Wild Animal Medicine, 7th ed: 537-543.
Willis TJ, Burgdorf-Moisuk A, Connolly M, Raines J, Ratliff C, Gyimesi ZS, Lipanovich E, Dumonceaux GA, Perrin KL, Howard LL, Kinney ME, Suedmeyer K, Latimer E, Kim TL, Watts JR, Tan J, Ling P. Elephant endotheliotropic herpesvirus 2 infection in 5 African elephants (Loxodonta africana) at multiple North American zoological institutions. Am J Vet Res. 2025 Jul 2;86(9).
